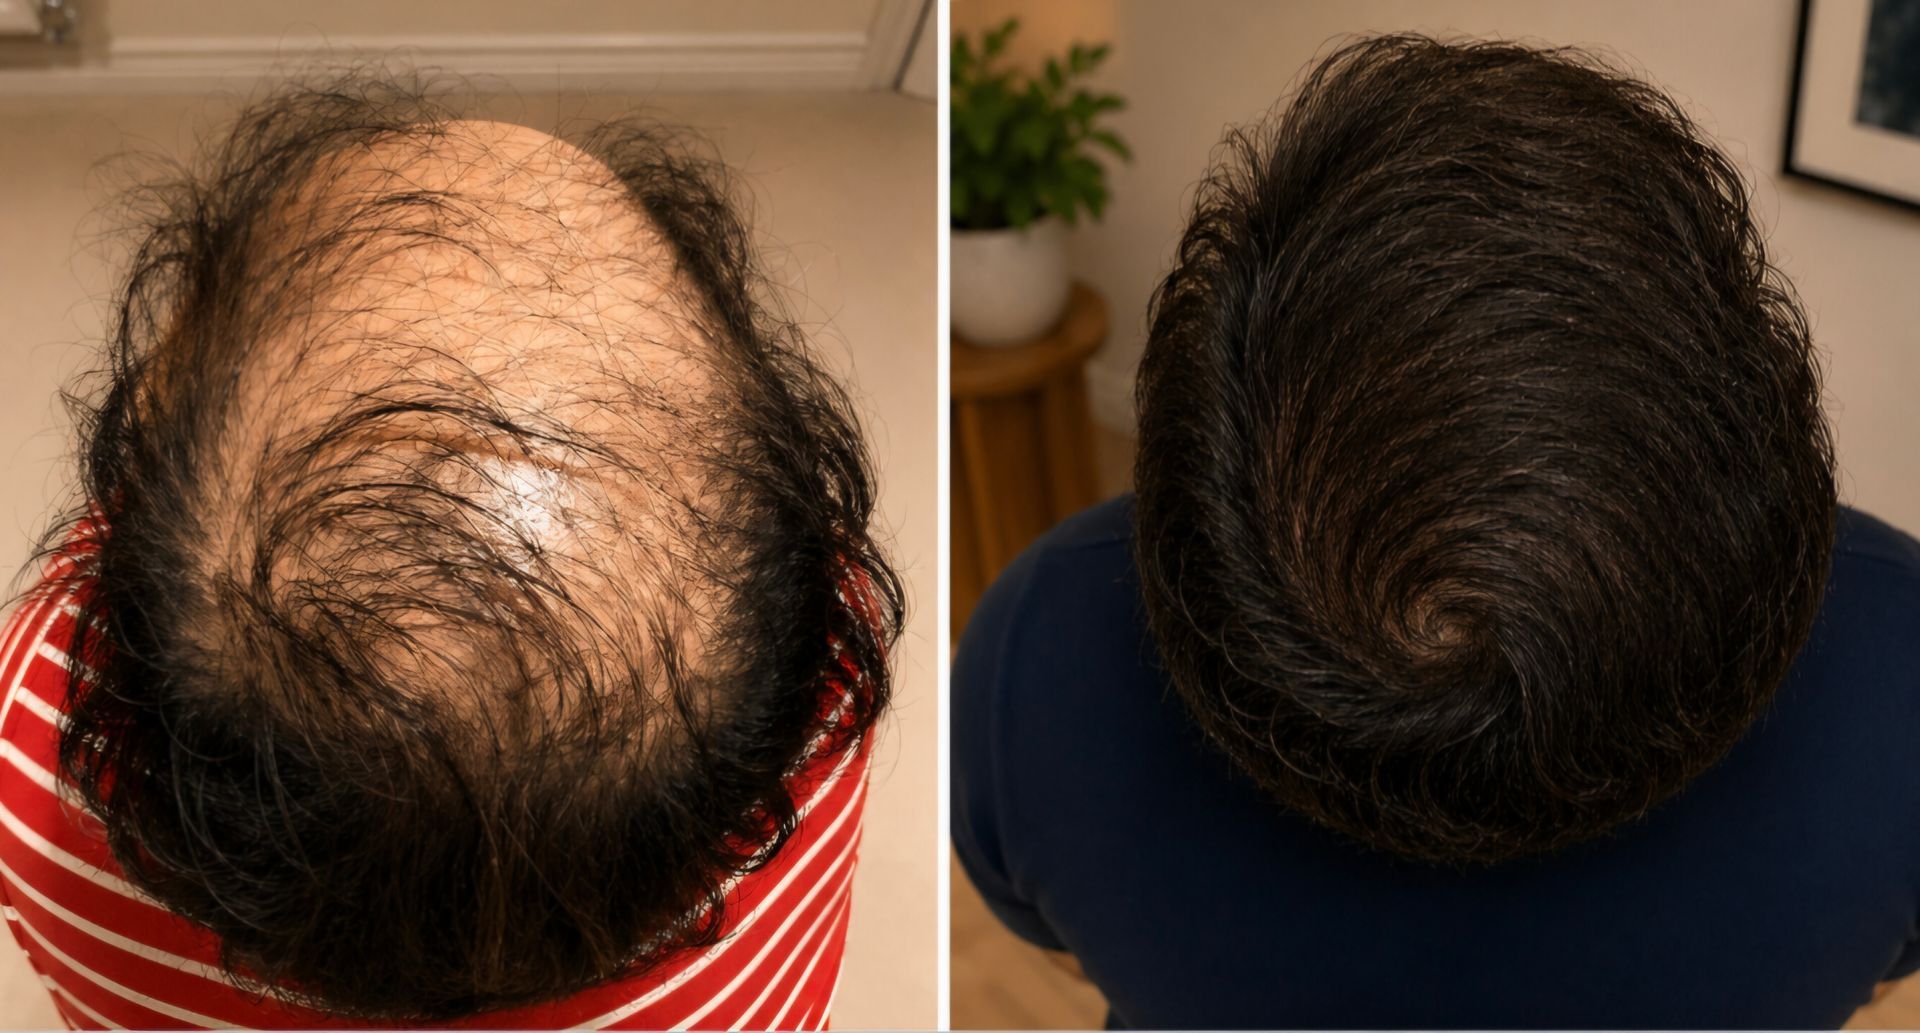
Sertraline and hair loss: what to discuss with your prescriber
Hair loss is a reported adverse effect, but a change during treatment does not establish the cause. Do not stop suddenly.


On this page
Hair loss is listed as an uncommon adverse effect in UK sertraline product information. If you notice shedding while taking it, speak to your prescriber. Do not stop sertraline abruptly or change the dose yourself: withdrawal symptoms and a return of the condition being treated are separate risks that need consideration.
What the product information says
A UK sertraline patient leaflet lists hair loss among uncommon effects, which may affect up to 1 in 100 people. This does not mean sertraline is the cause of every episode of thinning that occurs during treatment.
Check the leaflet supplied with your own medicine, since formulation and product information matter. A pharmacist can help you interpret it and identify which symptoms need prompt medical advice.
Why timing needs careful review
Write down when sertraline was started, any dose changes and when the shedding became noticeable. Include recent illness, weight changes, other medicines and supplements. Hair-cycle changes can take time to show, so the most recent event is not always the relevant one.
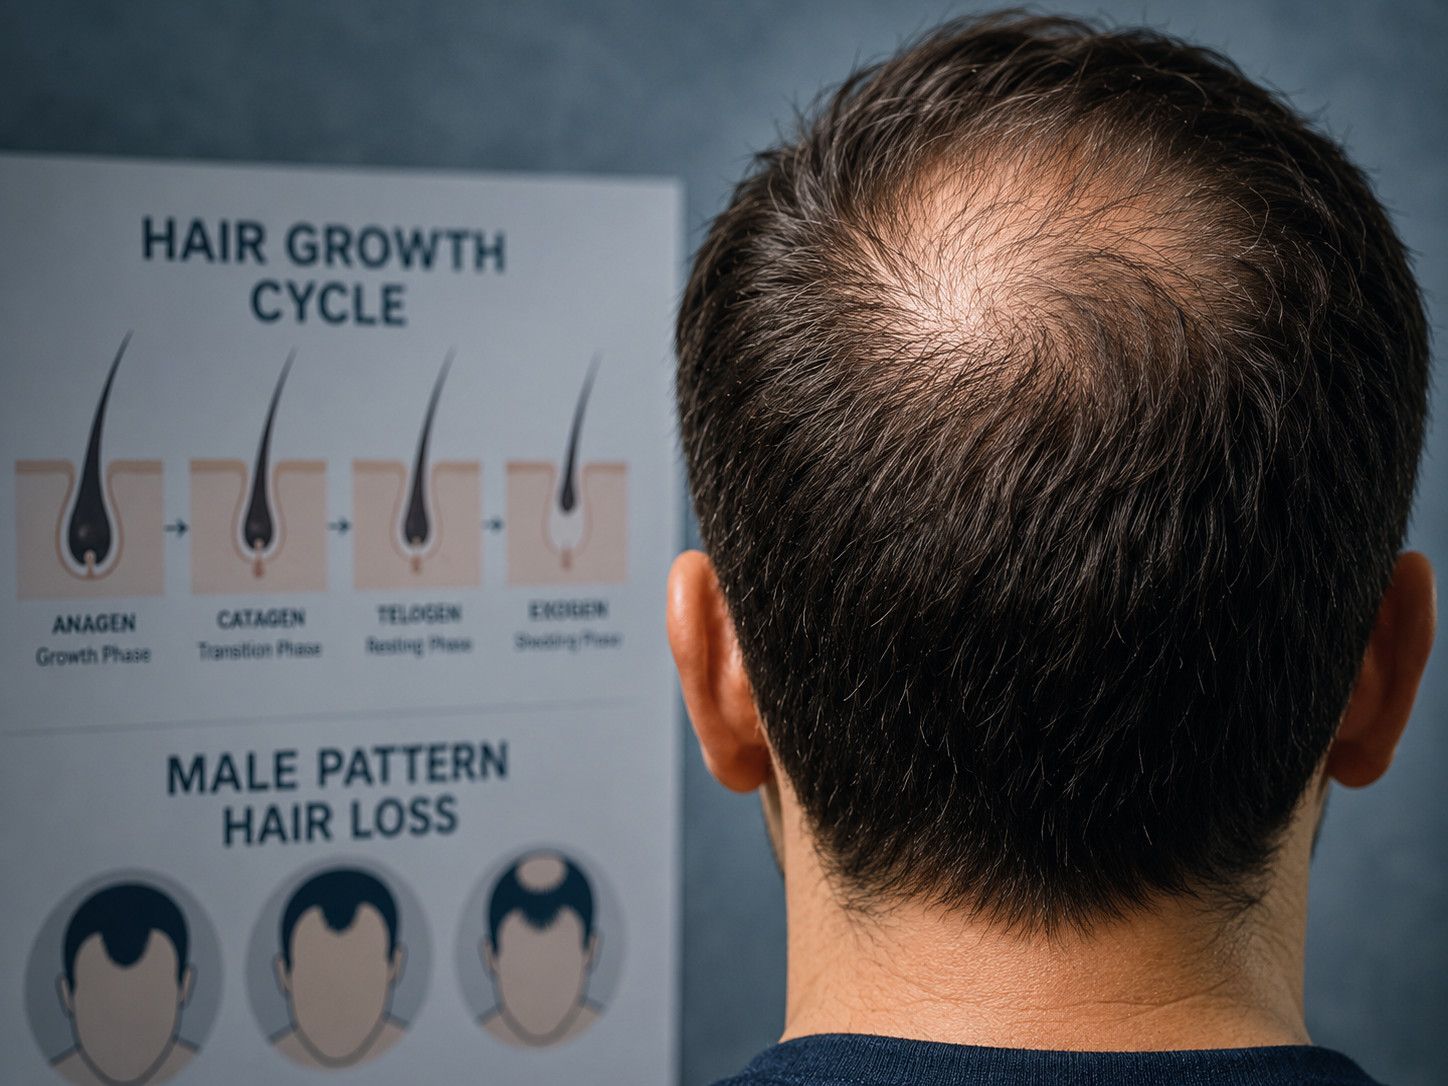
Diffuse shedding can occur with telogen effluvium, while gradual recession or a widening parting may suggest pattern loss. Scalp inflammation and other conditions also need consideration. More than one factor can be present.
A case report of one person improving after a medicine change cannot predict your own course. It does not establish which alternative would be appropriate for your mental health or whether your hair would recover on the same timetable.

What your prescriber may consider
The clinician can review the medicine's benefit, the severity and pattern of the hair change and other possible explanations. An examination or tests may be appropriate depending on the history. Any decision to continue, adjust or change treatment should weigh the whole clinical picture.
The NHS sertraline guidance advises against stopping suddenly and explains that a doctor can arrange gradual reduction when stopping is appropriate. Do not skip doses as a way of testing whether hair loss improves.
Preparing for the appointment
Bring your medication list and a short timeline. Comparable photographs may help show the change. Explain whether the hair loss is causing distress, especially if it affects your willingness to keep taking treatment.
Ask what will happen next, when the hair should be reviewed and which symptoms should prompt earlier contact. Avoid starting several new hair products before the review, as irritation or overlapping changes can make the picture less clear.
Will the hair grow back?
Recovery depends on the cause and whether another condition is present. If a medicine is contributing, improvement may follow a clinician-led change, but it cannot be guaranteed or timed precisely. Visible fullness takes longer to change than a prescription.
A transplant should not be the first response to unexplained active shedding. Establish the diagnosis and review the medical treatment before considering surgery.
Questions and answers
Should I stop sertraline if I see more hair in the shower?
No. Discuss it with your prescriber rather than stopping suddenly. Seek urgent help for severe symptoms or a mental-health crisis.
Does hair loss mean sertraline is damaging every follicle?
That conclusion cannot be drawn from shedding alone. The pattern and possible causes need assessment.
Is another antidepressant guaranteed not to affect my hair?
No guarantee should be made. The choice must consider effectiveness, adverse effects and your medical history, not hair loss in isolation.