The Norwood scale: what the stages tell you
The scale describes common patterns of male hair loss. It cannot predict your exact future or graft requirement.

On this page
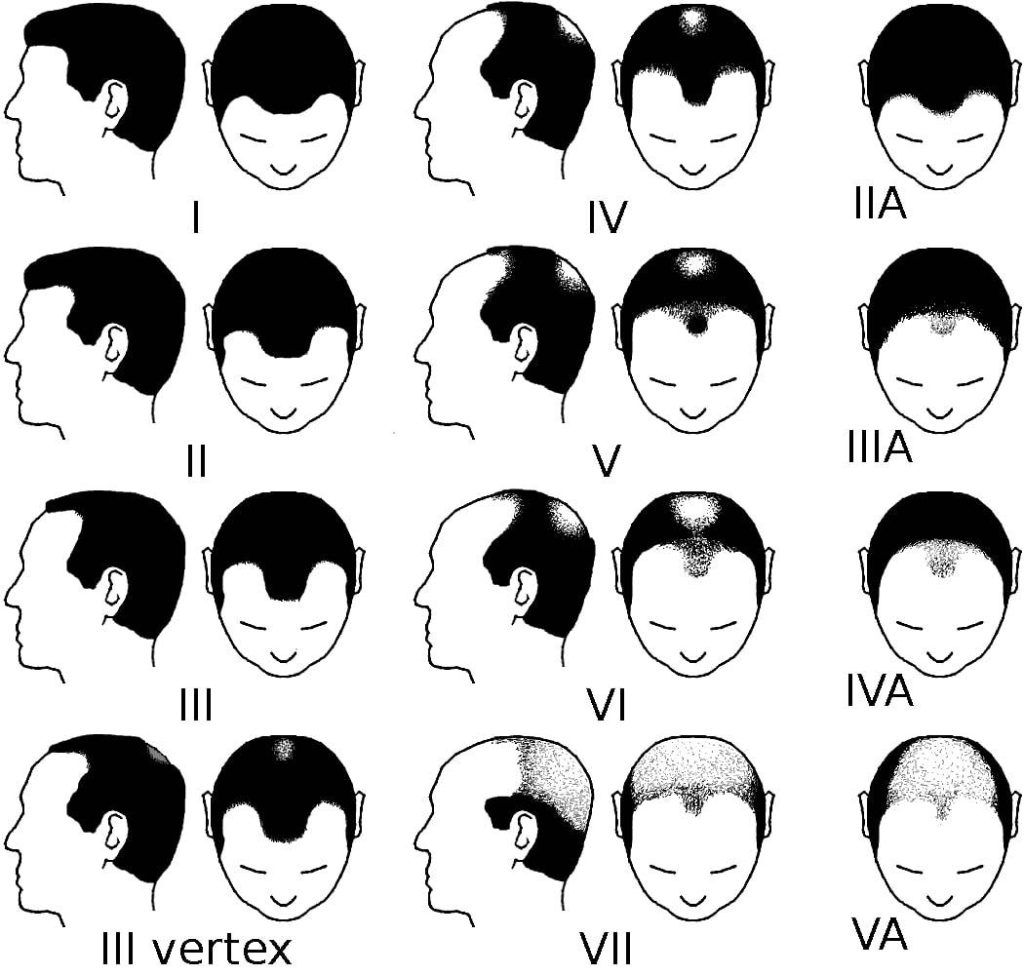
The Hamilton–Norwood scale describes common patterns of male pattern hair loss, from little recession to extensive loss across the top of the scalp. It helps clinicians communicate what they see. It does not diagnose every cause of thinning or tell you exactly how many grafts you need.
Understanding the stages
Stages I and II
Stage I describes little or no recession. Stage II describes a degree of recession at the temples. A photograph placed in one of these categories does not, on its own, establish whether the hairline is stable or changing.
Stage III and the vertex pattern
Stage III describes more marked frontal and temporal recession. The vertex variation describes loss around the crown. The distribution matters because a frontal outline and a crown whorl need different planning.
Stages IV and V
Loss at the front and crown is more extensive, with a band of hair still separating them. In stage V that bridge is narrower and the affected areas larger. The scale describes the visible pattern; it does not prove that a person will progress through every later stage.
Stages VI and VII
In stage VI, frontal and crown loss have joined. Stage VII describes extensive loss with a remaining band around the sides and back. The size and quality of that remaining donor region become especially relevant when considering surgery.
The British Association of Dermatologists' information on male pattern hair loss explains the underlying condition. Different classification systems and variations exist, so the clinical description is more useful than arguing over a borderline photograph.
Why the scale cannot give an exact graft count
Two people at the same stage may have different scalp sizes, donor density, hair thickness and curl. Their priorities may differ too: one may want to address the front, while another is more concerned about the crown.
A graft estimate needs measurements and a donor assessment. Ask how the number relates to the area and intended coverage. The donor-area guide explains why a high stage does not create permission to take unlimited grafts.
What it leaves out
The Norwood scale does not capture every pattern of diffuse thinning, inflammation, scarring or patchy loss. Nor does it measure the speed of change or the effect on your wellbeing. A diagnosis needs the history and examination as well as a description of the hairline.
A sore scalp, sudden patch or rapid shedding should not simply be assigned a Norwood number. Our alopecia guide explains some of the other conditions that may need consideration.
Using it to track change
Comparable photographs can help show whether the hairline or crown is changing over time. Keep lighting, angle and hair condition similar. The clinician can then consider the pattern alongside symptoms, family history and any treatment response.
The scale can support a discussion of medication, monitoring or surgery. It should not be used to sell a fixed “stage four package” without examining the donor region and discussing future loss.
Questions and answers
Will I inevitably reach stage VII?
No. The scale is a classification of patterns, not a timetable or a prediction that every person reaches its final stage.
Can I diagnose myself from an online chart?
A chart may help you describe your concern, but it cannot establish the cause of loss or replace an assessment.
Does stage III always need a transplant?
No. Suitability and personal preference matter. Observation, medication, cosmetic options or no treatment may be reasonable to discuss.